
Understand gastroparesis, a gastric motility disorder causing delayed stomach emptying. Explore idiopathic, diabetic, and postsurgical classifications.
Gastroparesis: Definition, Physiological Classifications, and Mechanics
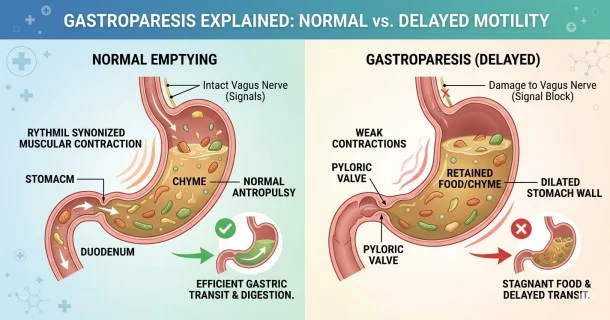
Gastroparesis is a chronic gastric motility disorder characterized by delayed gastric emptying of solids and liquids in the absolute absence of mechanical obstruction. The stomach typically relies on regular, highly coordinated muscular contractions to grind food particles and propel them into the duodenum. When these involuntary movements are weakened, slowed, or completely halted, the stomach cannot empty its content normally.
This digestive breakdown typically occurs when systemic disease, injury, or metabolic imbalances impair the vagus nerve, which serves as the primary neurological regulator of the gastrointestinal tract.
Normal Gastric Emptying Dynamics
To appreciate how motility disorders disrupt digestion, it is important to understand the three distinct mechanical phases of a healthy stomach:
- Proximal Stomach Accommodation: Following each swallow, the upper part of the stomach undergoes slow, sustained relaxation to accommodate incoming food without significantly increasing internal pressure.
- Distal Gastric Antral Grinding: The lower part of the stomach initiates rhythmic, synchronized contractions at a steady rate of roughly three beats per minute. This activity creates powerful fluid waves that splash food against the closed pyloric valve, grinding it into liquid chyme.
- The Interdigestive Migrating Motor Complex (MMC): Between meals, the stomach generates intense bursts of synchronized electrical waves accompanied by a wide opening of the pyloric sphincter. This vital phase acts as a "housekeeping wave" to sweep out larger, indigestible food fragments.
Clinical Classification of Gastroparesis
Gastroenterologists divide gastroparesis into three primary clinical categories based on the underlying driver of the neuromuscular impairment:
Idiopathic Gastroparesis
This is the most frequently diagnosed form of the disorder, referring to cases where standard clinical diagnostic panels cannot establish a definitive primary cause. Idiopathic gastroparesis exhibits an exceptionally high prevalence among young to middle-aged individuals, with women representing approximately 82% of all documented patients. Clinical observations suggest that natural variations in progesterone levels during the later stages of the menstrual cycle can subtly influence gastric smooth muscle contractility.
Diabetic Gastroparesis
A well-established systemic complication that typically arises in individuals with long-standing, poorly controlled Type 1 or Type 2 diabetes. Chronic hyperglycemia damages the microvascular networks that supply blood to the vagus nerve. This nerve damage prevents normal muscle stimulation, frequently occurring alongside other late-stage diabetic complications like diabetic retinopathy, nephropathy, and peripheral neuropathy.
Postsurgical Gastroparesis
This form develops as a direct consequence of accidental injury or intentional surgical alteration of the vagus nerve during major upper abdominal procedures. Common operations linked to postsurgical gastroparesis include peptic ulcer surgeries (such as a vagotomy with antrectomy), fundoplication for severe acid reflux, and various bariatric surgeries.
Explore Comprehensive Gastroparesis Guides
To navigate the specific diagnostic and management phases of this motility disorder, visit our detailed sub-sections:
- Gastroparesis Symptoms – Learn to identify the warning signs of delayed gastric emptying.
- Gastroparesis Causes & Triggers – Discover how systemic conditions disrupt your vagus nerve.
- Gastroparesis Diagnostic Testing – Read about gastric emptying studies and smart pill testing.
- Gastroparesis Treatment Options – Explore dietary adjustments, prokinetic drugs, and therapies.
Frequently Asked Questions (FAQ)
What is the difference between a mechanical stomach obstruction and gastroparesis?
A mechanical obstruction is a physical barrier—such as a large tumor, deep ulcer scar tissue, or an ingested bezoar mass—that physically blocks food from exiting the stomach cavity. Gastroparesis is a functional neuromuscular failure; the physical pathway out of the stomach is completely wide open, but the stomach muscles lack the neurological signals required to pump food through it.
Why is gastroparesis statistically more common in women than in men?
Epidemiological data shows that over 80% of idiopathic gastroparesis patients are female. While the exact systemic reasons are still being studied, clinical research indicates that women naturally exhibit slower baseline gastric emptying times than men. This difference is further amplified by hormonal fluctuations, particularly elevated levels of progesterone which act as a natural smooth muscle relaxant that can reduce stomach wall contractions.
Can a brief viral illness trigger long-term gastroparesis?
Yes. A specific subset of idiopathic gastroparesis is clinically recognized as post-infectious gastroparesis. This can occur after a severe, acute viral infection—such as Epstein-Barr virus, cytomegalovirus, or severe rotavirus gastroenteritis—which triggers a localized autoimmune response that temporarily inflames or damages the autonomic nerve cells regulating the stomach muscles.