
Understand peptic ulcer disease, including gastric, duodenal, and esophageal types. Learn about the 0.5 cm medical definition and global prevalence statistics.
Peptic Ulcer Disease: Definition, Classifications, and Prevalence
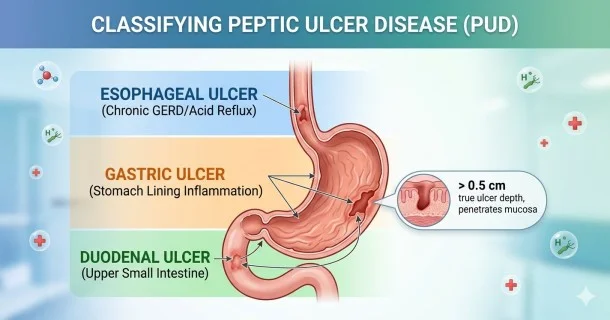
Peptic Ulcer Disease (PUD) is a highly prevalent gastrointestinal condition characterized by the formation of distinct, painful sores or mucosal breaks within the lining of the upper digestive tract. By strict medical definition, a true peptic ulcer is a deep erosion that penetrates through the muscularis mucosae layer of the tissue, resulting in a localized breakdown that measures equal to or greater than 0.5 cm in diameter.
These lesions develop primarily in areas exposed to highly concentrated gastric juices, where aggressive factors like hydrochloric acid and pepsin overpower the protective mechanisms of the mucous membrane.
Anatomical Classifications of Peptic Ulcers
Gastroenterologists classify peptic ulcers into three distinct categories based on their exact anatomical location within the upper digestive tract:
Gastric Ulcers
These are localized mucosal sores that develop directly on the inner lining of the stomach wall. Gastric ulcers are highly sensitive to acid fluctuations and often cause discomfort that is heavily influenced by the presence of food in the stomach.
Duodenal Ulcers
These sores form in the duodenum, which is the first and most proximal section of the small intestine immediately following the stomach's pyloric valve. Duodenal ulcers are exceptionally common and frequently correlate with a localized hypersecretion of gastric acids.
Esophageal Ulcers
A less common form of peptic ulceration that develops at the lower end of the esophagus, the muscular tube connecting the mouth to the stomach. These lesions are almost exclusively caused by chronic chemical irritation from severe gastroesophageal reflux disease (GERD).
Key Epidemiological Data and Global Prevalence
Peptic ulcer disease is a global health concern affecting millions of individuals across all demographics, age groups, and socioeconomic statuses.
- Lifetime Prevalence: Epidemiological data indicates that approximately 10% of the global population will develop a peptic ulcer at some point in their lifetime. Globally, the disease accounts for millions of clinical presentations annually.
- H. Pylori Correlation: The vast majority of documented peptic ulcer cases are driven by underlying systemic triggers. Historically, chronic colonization by Helicobacter pylori bacteria accounts for roughly 70% of gastric ulcers and up to 90% of duodenal ulcers.
- Clinical Mortality Metrics: While modern acid-suppression therapies have drastically reduced overall mortality rates to around 1 in 10,000 cases, the development of severe acute complications remains dangerous. Specifically, the clinical mortality rate associated with unchecked upper gastrointestinal ulcer bleeding sits at approximately 5%.
Explore Comprehensive Peptic Ulcer Guides
To navigate the specific phases of this condition, visit our detailed clinical sub-sections:
- Peptic Ulcer Symptoms – Learn to identify the difference between gastric and duodenal pain cycles.
- Peptic Ulcer Causes & Triggers – Understand how H. pylori and NSAID overuse strip the stomach's defense.
- Peptic Ulcer Diagnostic Testing – Read about what to expect during an upper endoscopy check.
- Peptic Ulcer Treatment Options – Discover the medical therapies used to heal mucosal tissue.
Frequently Asked Questions (FAQ)
What is the exact difference between a mucosal erosion and a peptic ulcer?
A mucosal erosion is a shallow, superficial scratch or irritation that only impacts the outermost layers of the tissue lining and typically heals quickly without complications. A true peptic ulcer is a deeper, more severe break that penetrates through the muscularis mucosae layer of the tract, measuring at least 0.5 cm across, and requires targeted medical treatment to heal.
How do doctors clinically differentiate between a gastric ulcer and a duodenal ulcer based on pain?
While both cause a burning sensation in the upper abdomen, the timing of the pain is a major clinical clue. Gastric ulcer pain is often aggravated shortly after eating due to the physical friction of food and acid secretion. Conversely, duodenal ulcer pain typically occurs 2 to 3 hours after a meal when the stomach is empty, and it is often temporarily relieved by eating or taking antacids.
Who is at risk for developing severe complications from peptic ulcer disease?
While peptic ulcers can affect individuals of any age or gender, senior adults over the age of 65, chronic users of high-dose NSAID pain relievers, individuals with a history of recurrent ulcers, and those with advanced systemic illnesses (like liver or kidney disease) carry a significantly higher risk for life-threatening ulcer bleeding or wall perforation.