
Explore clinical esophagitis treatment options, including acid suppressants, antimicrobial therapies, esophageal dilation, and advanced surgical interventions.
Esophagitis Treatment: Clinical Interventions and Medications
The primary goal of esophagitis treatment is to reduce ongoing mucosal irritation, alleviate painful symptoms, resolve the root cause of injury, and prevent long-term complications like esophageal strictures. Therapeutic strategies vary significantly depending on whether the tissue damage stems from mechanical, chemical, infectious, or immune-mediated pathways.
Esophagitis Medication Options
Pharmacological management is tailored strictly to the underlying etiology determined during clinical diagnosis:
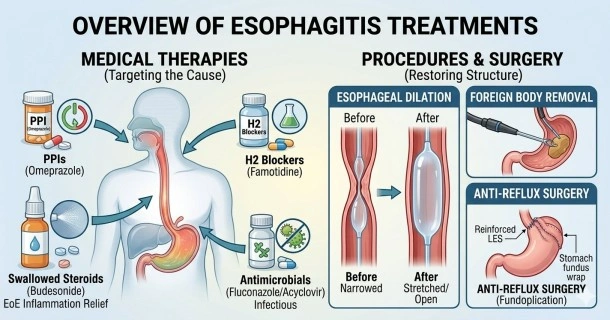
Acid-Suppressive Medications for Reflux Esophagitis
When esophagus inflammation is caused by Gastroesophageal Reflux Disease (GERD), neutralizing or shutting down gastric acid production is critical to give the esophageal mucosa an environment to heal:
- Proton Pump Inhibitors (PPIs): The gold standard clinical option for healing erosive tissue damage. PPIs significantly shut down acid production at the source. Common options include omeprazole, lansoprazole, pantoprazole, and esomeprazole.
- H2 Receptors Antagonists (H2RA / H2 Blockers): Used for less severe cases or as adjunctive therapies. These block histamines that prompt the stomach to secrete acid. Common variants include famotidine and cimetidine.
- Antacids: Over-the-counter options like calcium carbonate provide rapid, transient chemical neutralization of acid pools, offering temporary symptom relief but not long-term tissue healing.
Antimicrobial Therapies for Infectious Esophagitis
If an active infection is attacking the esophageal lining, specific targeted antimicrobial agents are required:
- Antifungal Regimens: Infectious esophagitis triggered by Candida yeast overgrowth is treated with systemic antifungals such as fluconazole.
- Antiviral Regimens: Tissue inflammation resulting from Herpes Simplex Virus (HSV) or Cytomegalovirus (CMV) is managed with specialized antivirals like acyclovir or ganciclovir.
Targeted Therapies for Eosinophilic Esophagitis (EoE)
Managing allergic or immune-mediated tissue swelling involves calming the focal immune reaction:
- Topical/Swallowed Corticosteroids: Medications like fluticasone or budesonide are swallowed rather than inhaled, coating the esophageal tissue to suppress localized eosinophilic inflammation directly.
- Biologic Agents: Advanced cases may be treated with targeted monoclonal antibody therapies, like dupilumab, which specifically block the inflammatory pathways driving the allergic response.
Advanced Endoscopic and Surgical Procedures
When chronic inflammation goes untreated or fails to respond to standard medical therapies, advanced structural or surgical procedures become necessary to restore proper swallowing mechanics:
Esophageal Dilation (Stretching)
Chronic inflammation can cause heavy scar tissue to form along the inner wall, resulting in an anatomical narrowing known as an esophageal stricture. During an upper endoscopy, a gastroenterologist can carefully guide a specialized dilator balloon or silicone bougie tube down the esophagus to gently stretch the stricture, significantly relieving dysphagia (swallowing difficulty).
Foreign Body Removal
Acute blockages caused by large food particles or impacted medication fragments getting caught in a narrow, inflamed esophagus require emergency upper endoscopy. The physician uses miniature retrieval tools to clear the obstruction safely.
Surgical Interventions
If a patient has severe reflux esophagitis that is completely unresponsive to maximum medical therapy, or is complicated by a large hiatal hernia, anti-reflux surgery may be recommended:
- Fundoplication: A surgical procedure (often laparoscopic) where the upper part of the stomach (the fundus) is wrapped around the lower end of the esophagus. This mechanically reinforces the weak lower esophageal sphincter (LES) to permanently prevent acid from washing upward.
Frequently Asked Questions (FAQs)How long does it take for an inflamed esophagus to heal?
With consistent proton pump inhibitor (PPI) therapy or proper root cause management, mild to moderate esophagitis can show significant tissue healing within 4 to 8 weeks. Severe damage or chronic strictures may require a longer treatment window or procedural care.
Can esophagitis be cured without surgery?
Yes. The vast majority of esophagitis cases are successfully resolved using targeted lifestyle changes and specific daily medications (like acid suppressants or anti-infective therapies). Surgery is typically reserved for complex cases involving severe tissue scarring or anatomy faults like structural hiatal hernias.
Why was ranitidine (Zantac) removed from modern esophagitis treatments?
Ranitidine (formerly a popular H2 blocker option) was widely recalled and permanently discontinued globally due to safety concerns regarding the presence of NDMA, a probable human carcinogen. Modern medical practices now use safer, highly stable alternative H2 blockers like famotidine instead.