
Explore what causes pyloric stenosis. Learn about the genetic factors and antibiotic exposures in infants, as well as peptic ulcer scarring in adults.
Pyloric Stenosis Causes: What Triggers the Obstruction?
The exact underlying cause of pyloric stenosis is not yet fully understood by medical scientists. However, clinical research shows it develops from a complex interplay of genetic predisposition and environmental factors. This condition leads to progressive thickening and hypertrophy of the circular muscle fibers within the pyloric sphincter, physically blocking food from exiting the stomach.
While the infant form stems from abnormal muscle development, adult cases are entirely acquired.
What Causes Pyloric Stenosis in Infants?
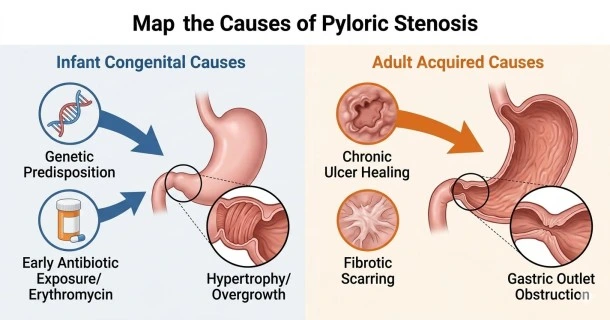
In newborns, the condition occurs due to cellular hyperplasia and hypertrophy of the pyloric valve. While no single gene or trigger is isolated, several well-documented risk factors heavily influence its development:
1. Genetic Predisposition and Family History
Genetics play a powerful role in a baby's likelihood of developing the condition.
- Family Risk: Approximately 15% of infants diagnosed with the condition have a direct biological family history of it.
- The Gender Disparity: Male infants face a much higher risk, developing the condition at a 4:1 ratio compared to females. Firstborn males are statistically the most vulnerable group.
2. Early Antibiotic Exposure
Exposure to specific medications during critical developmental windows is strongly linked to muscle thickening.
- Infant Exposure: Giving a baby certain macrolide antibiotics—most notably erythromycin—within the first few weeks of life significantly increases their risk.
- Maternal Exposure: Babies born to mothers who took macrolide antibiotics during late pregnancy also show a higher incidence rate.
3. Environmental and Lifestyle Influences
- Maternal Smoking: Smoking cigarettes during pregnancy impairs normal fetal development and increases the risk of infant hypertrophic pyloric stenosis by 1.5 to 2 times.
- Feeding Methods: Some studies suggest that bottle-feeding might increase risks compared to exclusive breastfeeding, potentially due to rapid gastric emptying or structural muscle overstimulation.
What Causes Pyloric Stenosis in Adults?
Unlike the congenital developmental form seen in babies, adult pyloric stenosis is an acquired condition. It develops secondary to chronic, long-standing structural damage in the upper digestive tract:
- Peptic Ulcer Disease (PUD): This is the most common cause of adult pyloric stenosis. Chronic, recurring ulcers caused by severe H. pylori infections or heavy use of Nonsteroidal Anti-inflammatory Drugs (NSAIDs) lead to deep tissue erosions.
- Fibrotic Scar Tissue: As the body repeatedly attempts to heal these chronic ulcers, rigid fibrotic scar tissue forms around the pyloric channel. Over time, this scarring contracts, severely narrowing the opening and creating a gastric outlet obstruction.
- Inflammatory Hypertrophy: The surrounding pyloric muscles may also undergo work hypertrophy as they strain harder to force food past the rigid, scarred blockage.
Frequently Asked Questions (FAQs)
Is pyloric stenosis caused by something the mother did wrong during pregnancy?
No. Aside from avoiding cigarette smoking and unprescribed macrolide antibiotics, there is nothing a mother can do to prevent or cause this condition. It is a complex developmental anomaly driven primarily by genetics and involuntary environmental factors.
Can a severe H. pylori infection cause pyloric stenosis?
Yes, but typically only in adults. In adults, long-standing, untreated H. pylori infections cause chronic peptic ulcers. The repeated healing and scarring cycles of these ulcers eventually narrow the pylorus, leading to secondary adult pyloric stenosis.
Why does early antibiotic use trigger pyloric stenosis in babies?
Macrolide antibiotics like erythromycin are believed to interact directly with motilin receptors in the infant's gastrointestinal tract. This interaction can cause strong, sustained contractions of the pyloric sphincter, eventually leading to muscle thickening and hypertrophy.
Does bottle-feeding directly cause the pyloric muscle to thicken?
No, bottle-feeding is not a direct cause, but it is an identified risk factor. The mechanical action of drinking larger volumes of milk more rapidly from a bottle may overstimulate the infant's pyloric valve, inducing work hypertrophy in genetically predisposed infants.